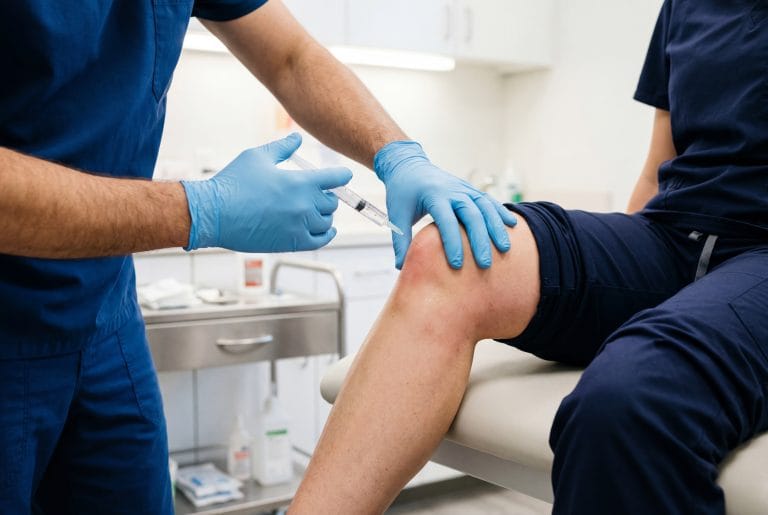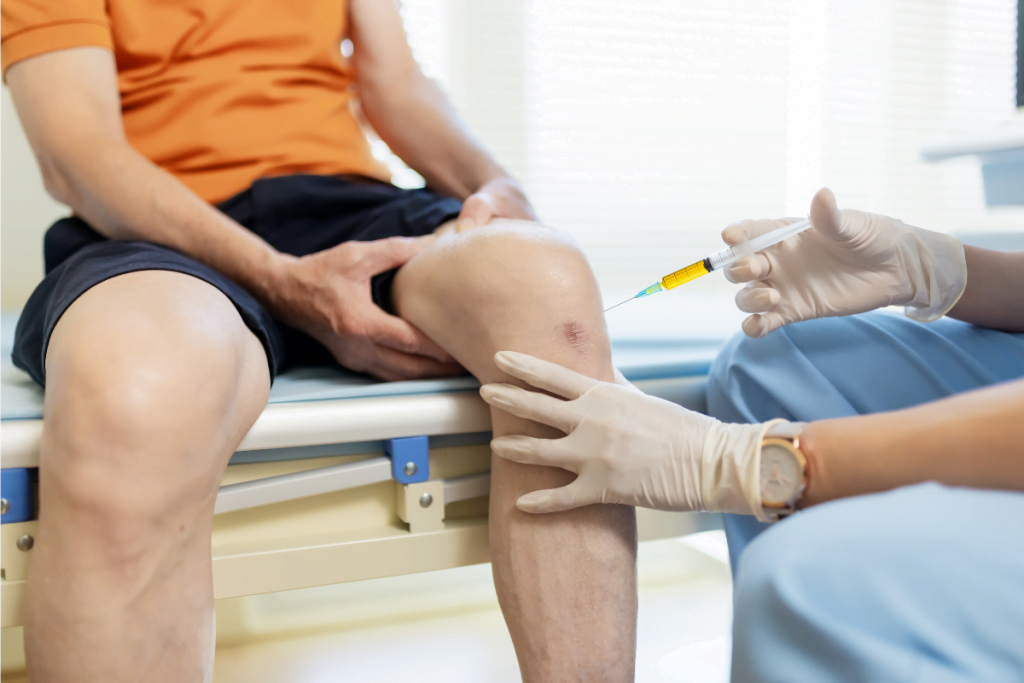
Orthovisc is a high-molecular-weight hyaluronan given as an intra-articular knee injection. It is not a corticosteroid. US labeling covers pain from osteoarthritis of the knee in patients who have not responded adequately to conservative non-pharmacologic therapy and simple analgesics such as acetaminophen. Clinic teams evaluating orthovisc injections should expect modest and variable symptom benefit, mostly local and self-limiting adverse events, and major guideline bodies that disagree about routine use. That disagreement drives much of what you will field in clinic: patient questions, payer documentation requests, and denials.
Why it matters: Setting expectations before the first syringe is opened prevents most of the disappointment and most of the follow-up calls.
The Short Version
- Class: non-animal, non-cross-linked hyaluronan, produced by bacterial fermentation.
- Indication: knee osteoarthritis pain after conservative care has failed, per the approved labeling.
- Course: a series of weekly injections, with the exact number stated in the current package insert.
- Typical reactions: transient injection-site pain, joint swelling, stiffness and warmth.
- Red flag: fever with a hot, rapidly swelling knee needs urgent assessment for septic arthritis.
What Orthovisc Is and How It Works
Hyaluronan is a normal constituent of synovial fluid and cartilage matrix. In osteoarthritic joints, the concentration and molecular weight of native hyaluronan fall, and synovial fluid loses viscoelasticity. Viscosupplementation aims to restore some of those rheologic properties for a period after injection. Laboratory work also describes anti-inflammatory and mechanoprotective signaling effects, but those mechanisms are not a reliable predictor of symptom response in an individual patient.
Orthovisc is a sterile, pyrogen-free solution of high-molecular-weight hyaluronan derived by bacterial fermentation rather than from avian tissue. Per the manufacturer’s instructions for use, each single-use syringe delivers 30 mg of hyaluronan in 2 mL for intra-articular use in the knee. Because the source is non-avian, egg or feather protein allergy is not the screening question it once was for this class. Known hypersensitivity to hyaluronate preparations remains a contraindication.
Is it a steroid?
No. Patients often arrive expecting “a cortisone shot,” and the distinction changes counseling. Intra-articular corticosteroids act quickly and tend to fade over weeks. Hyaluronan products work differently, usually with slower onset over the series and no systemic glucocorticoid effects, so there is no concern about glycemic spikes, skin atrophy, or steroid-related cartilage questions. Saying this plainly at the first visit avoids a mid-series complaint that the injection “did not work right away.”
Regulatory Status and Where the Device Sits
In the United States, viscosupplements of this type are regulated as Class III medical devices approved through the premarket approval pathway, not as drugs. Approval is specific to the knee. Use in the hip, shoulder, ankle, thumb carpometacarpal joint or any other site is off-label, and should be treated as such in consent, documentation and billing. Approval status and labeled wording can change, so verify the current device record and insert rather than a secondary summary. Device approvals are searchable in the FDA premarket approval database, which is the authoritative record for status and labeling supplements: FDA PMA database.
What the Evidence Says About Benefit
Benefit is real for some patients and modest on average, which is why reputable guidelines land in different places. The American Academy of Orthopaedic Surgeons advises against routine use of intra-articular hyaluronic acid for symptomatic knee osteoarthritis in its clinical practice guideline, citing pooled effects that fall short of clinically important thresholds; see the AAOS knee osteoarthritis guideline. The American College of Rheumatology likewise issues a conditional recommendation against hyaluronan injection for knee osteoarthritis in its management guideline, available through the ACR clinical practice guidelines. Other international groups describe the evidence as uncertain rather than negative, and note heterogeneity across products, molecular weights and trial designs.
Practical reading for a clinic: hyaluronan is not a first-line therapy and should not be presented as disease-modifying. It is one option in the gap between failed conservative care and arthroplasty, particularly for patients who cannot take NSAIDs, who respond poorly or briefly to corticosteroid, or who are deferring surgery. Frame the conversation around a trial of therapy with a defined review point, not a guaranteed result.
Why patient-reported experiences vary so much
Online reviews of this product class swing widely, and the reasons are explainable. Radiographic severity matters; patients with bone-on-bone, Kellgren-Lawrence grade 4 disease generally respond less well than those with mild to moderate changes. Large effusions, uncorrected malalignment, inflammatory arthropathy and central sensitization all blunt response. Expectation also matters. A patient told to expect relief within 48 hours will call the clinic disappointed; a patient told that benefit, if it comes, usually builds over several weeks will not.
Patient Selection and Contraindications
Select for the label first. The approved population is knee osteoarthritis pain that has not responded adequately to non-pharmacologic measures and simple analgesics. Confirm the diagnosis radiographically, document what conservative care has already been tried and for how long, and record baseline pain and function so the series can be judged objectively.
Per the instructions for use, do not inject in these situations:
- Known hypersensitivity to hyaluronate preparations.
- Infected or severely inflamed knee, or suspected septic arthritis.
- Skin disease or infection at or near the injection site.
Safety has not been established in pregnancy, in breastfeeding, or in children, so these groups fall outside the labeled population. Anticoagulation is not an absolute barrier for intra-articular injection in most practice settings, but it should be assessed individually and documented. Some hyaluronan labels in this class carry additional precautions, including caution with venous or lymphatic stasis in the affected limb; always read the insert in hand rather than relying on memory across brands.
Running the Injection Series Safely
This section describes published label-level considerations, not a substitute for hands-on training or your institution’s protocol.
The course is given as weekly injections on a fixed schedule stated in the current package insert. Consistency matters: missed weeks stretch the course and complicate both assessment and payer review. Strict aseptic technique is standard. If a significant effusion is present, aspirate before injecting; leaving a tense effusion dilutes the product and worsens post-injection discomfort. One class-specific point is easy to miss: avoid skin preparation agents containing quaternary ammonium salts, because hyaluronan can precipitate in their presence.
Post-injection counseling is short and should be consistent across staff. Advise avoiding strenuous or prolonged weight-bearing activity, such as running, tennis or heavy lifting, for roughly 48 hours. Ice and acetaminophen are reasonable for transient soreness where appropriate for that patient. Tell the patient which number to call, and what symptoms warrant calling the same day.
Repeat courses
Labeling addresses a defined course rather than indefinite repetition. Whether and when to repeat is a clinical judgment informed by the documented response to the first series, and in practice it is also shaped by payer rules on minimum intervals. Record the response before committing to another course.
Side Effects, Warning Signs and Escalation
Most adverse events reported with viscosupplementation are local, mild and short-lived. The commonly described reactions include injection-site pain, joint pain, transient swelling or effusion, stiffness, warmth and local erythema. These usually settle within a few days with rest, ice and simple analgesia. Systemic effects are uncommon with intra-articular hyaluronan.
Two situations deserve a clear clinic pathway.
The first is an acute inflammatory flare after injection, sometimes described as a pseudoseptic reaction: a painful, swollen, warm knee appearing within hours to a day or two of injection, without systemic infection. It is reported across the class and has been described more often with cross-linked products. Management is supportive and may include aspiration for diagnosis and symptom relief.
The second is septic arthritis, which is rare but joint-threatening. The features that should trigger urgent assessment are fever or chills, severe and rapidly escalating pain, a rapidly increasing effusion, spreading erythema, and inability to bear weight. The escalation path should be written down and known to front-desk staff: same-day clinical review, aspiration with Gram stain, cell count and culture, and urgent orthopedic or emergency referral when infection is suspected. Do not wait for a routine follow-up slot.
Quick tip: Give every patient a written post-injection card listing the three symptoms that mean call today, plus the number to call after hours.
How It Compares With Other Viscosupplements
Products in this class differ in source, molecular weight, whether the hyaluronan is chemically cross-linked, and how many injections make up a course. Some are derived from avian tissue; others, including this one, are produced by bacterial fermentation. Course length ranges from a single injection to three or five weekly injections, depending on the product. Head-to-head evidence establishing the superiority of any one formulation is limited, so differences in the published trials should be read with caution.
For a clinic, the practical discriminators are usually not pharmacologic. They are the number of visits a patient must attend, whether the product is covered by the plans you see most, whether the joint being treated is on-label, and how the syringe handles. A five-visit course and a single-injection course create very different scheduling and adherence profiles for the same patient. Choose on fit, document the reasoning, and avoid implying to patients that one brand is clinically superior without evidence that supports it.
Coverage Documentation, Storage and Sourcing
Denials in this category are usually documentation problems rather than clinical ones. Payers commonly ask for radiographic confirmation of osteoarthritis, a stated duration of symptoms, a specific record of failed conservative therapy including physical therapy and analgesics, prior corticosteroid response, baseline functional scores, and a minimum interval since any previous course. Build those fields into the pre-authorization template so nothing is retrieved from memory after the fact.
Storage is simple but must follow the current insert: keep syringes within the stated temperature range, do not freeze, protect from light, and discard any syringe that has been frozen or whose packaging integrity is compromised. Syringes are single-use and sterile; never resterilize or save a partially used syringe for a second patient. Record lot number and expiry in the patient record at the time of injection so that any recall can be traced quickly.
On sourcing, verify that the product you receive carries current US labeling and an intact package insert, and that lot and expiry are legible on arrival. Med Wholesale Supplies is a wholesale supplier of aesthetic, orthopedic and medical products to clinics, hospitals and medical professionals, operating since 2013.
Clinic Checklist
- Confirm the indication: knee osteoarthritis, conservative care documented as inadequate.
- Screen contraindications: hyaluronate hypersensitivity, joint infection, local skin infection.
- Record a baseline: pain score, function measure, effusion status, radiographic grade.
- Check the insert: course length, volume, storage range and precautions for the lot in hand.
- Prepare the field: aseptic technique; avoid quaternary ammonium disinfectants.
- Aspirate first when a significant effusion is present.
- Counsel consistently: 48 hours of reduced loading, expected soreness, when to call.
- Document per injection: date, site, lot, expiry, any immediate reaction.
- Review after the series against the baseline before deciding on repeat treatment.
Used this way, orthovisc injections fit a narrow but legitimate role: a documented trial of therapy for knee osteoarthritis pain in patients who have exhausted conservative options, delivered with clear expectations and a clean escalation pathway. Verify composition, course and storage against the current manufacturer instructions for use before every series, and keep the guideline position in view when counseling patients about likely benefit.
This content is for general informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a qualified clinician or pharmacist about your situation, and seek urgent care or call your local emergency number for severe or worsening symptoms.